
Advanced Evaluation and Treatment of Structural Heart Disease and Complex Cardiac Conditions
What Is Structural Heart Disease?
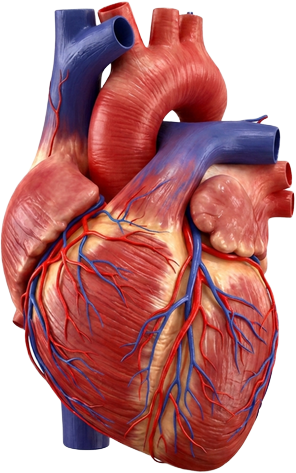
Structural heart disease refers to abnormalities in the heart’s physical architecture, including its valves, chambers, walls, and major vessels. These conditions may be present at birth or develop over time due to ageing, hypertension, infection, or progressive degenerative changes.
Unlike coronary artery disease, which restricts blood flow through narrowed vessels, structural heart disease affects the heart’s mechanical ability to pump blood. Symptoms do not always indicate the true severity of the underlying condition. Patients may remain relatively well for extended periods despite progressive structural deterioration. Others may experience severe symptoms even when standard imaging suggests only moderate disease. Accurate assessment involves integrating imaging findings with the patient’s clinical status and exercise capacity. In selected cases, it also requires direct hemodynamic measurements obtained through cardiac catheterisation.
Other Services
Conditions Treated
Aortic Valve Disease
Progressive narrowing of the aortic valve that increases strain on the left ventricle and requires careful assessment to determine the right time for intervention.
Tricuspid Valve Disease
Tricuspid regurgitation and stenosis affect right heart function and are often underdiagnosed, making careful haemodynamic assessment essential for effective management.
Unexplained Breathlessness with Suspected Cardiac Cause
Unexplained breathlessness may result from elevated heart filling pressures or diastolic dysfunction, which invasive haemodynamic assessment can detect when non-invasive tests are inconclusive.
Pre-Operative Cardiac Assessment
Specialist evaluation of cardiac risk, haemodynamic status, and functional reserve before major non-cardiac surgery, particularly in patients with known or suspected structural heart disease.
Mitral Valve Disease
Mitral stenosis and regurgitation affect heart and lung pressures, requiring integrated imaging and haemodynamic assessment to guide treatment.
Cardiac Chamber Abnormalities
Enlargement, thickening, or dysfunction of the heart chambers caused by valve disease, pressure overload, or ischaemia, often presenting with breathlessness, reduced exercise tolerance, or arrhythmia.
Heart Murmurs
Incidentally detected or symptomatic murmurs requiring specialist evaluation to exclude haemodynamically significant valvular pathology
Advanced Diagnostic Assessment
Echocardiographic Analysis
Detailed specialist interpretation of transthoracic and transoesophageal echocardiographic studies, assessing valve morphology, stenosis severity, regurgitant fraction, chamber dimensions, and systolic and diastolic function. Echocardiography forms the primary imaging foundation of structural heart disease evaluation.
Right Heart Catheterisation
The gold standard for direct haemodynamic assessment, performed in the catheterisation laboratory via venous access. It provides direct measurement of pressures throughout the right heart and pulmonary circulation, as well as cardiac output. These measurements are essential in complex valve disease, unexplained breathlessness, and pre-operative risk assessment. Over 200 right heart catheterisations have been performed at Level 3 independent competence.
Coronary Angiography as Part of Structural Assessment
Coronary artery disease frequently coexists with structural heart disease and must be assessed before any valve intervention is planned. Coronary angiography is integrated into the pre-intervention assessment pathway where clinically appropriate.
Haemodynamic Exercise Assessment
In selected patients, resting measurements do not fully reflect the physiological burden of structural disease during activity. Exercise haemodynamic assessment can reveal elevated filling pressures and abnormal pulmonary responses that are absent at rest, refining the indication for intervention.
Procedures and Interventions
Right Heart Catheterisation
This procedure is performed under local anesthesia through venous access to directly measure pressures within the right heart and pulmonary arteries and calculate cardiac output. It takes 30 to 60 minutes to complete and does not require general anesthesia or an overnight hospital stay.
Coronary Angiography
Performed as part of pre-intervention structural assessment to characterise the coronary circulation and determine whether revascularisation is required alongside structural intervention.
Structural Intervention Assessment and Referral
Patients requiring valve repair or replacement receive comprehensive pre-procedural assessment and detailed treatment planning, with coordinated referral to the appropriate specialist through a multidisciplinary team.
International Expertise. Precision Cardiovascular Care.
200+ Right Heart Catheterisations
Advanced Haemodynamic Assessment
Specialist Valve Disease Evaluation
Pre-Operative Cardiac Assessment